What the Anion Gap Indicates
The anion-gap value is a derived number that assists clinicians in understanding acid-base balance and identify hidden electrolyte disturbance. It is based on routine laboratory values from a blood test and shows the gap between measured positively charged ions and negatively charged ions in the blood.
In practice, the calculation uses serum sodium, chloride levels, and bicarbonate, with potassium levels sometimes included depending on the formula. The result offers insight into unmeasured anions that may be accumulating during illness. Because of that, the anion gap is a useful clinical tool for evaluating an acidotic condition and narrowing the causes of acid buildup.
Most clinicians first review a basic metabolic panel or a gas result when acid-base problems are suspected. The anion gap can then help determine whether the patient has high anion gap metabolic acidosis or non–anion gap metabolic acidosis. That distinction matters because the underlying causes, severity, and next steps can be very different.
Although the calculation is simple, the interpretation is not. The value is only one piece of the broader clinical assessment of the patient’s condition. It should be considered alongside symptoms, medications, kidney function, glucose, lactate, ketones, and other test results.
How to Use an Anion Gap Calculator
An anion gap calculator streamlines the gap calculation so you can rapidly understand the result from a blood chemistry panel. To use it, enter the serum sodium, chloride, and bicarbonate values. Some calculators also allow entry of albumin and potassium, which enhances accuracy in certain cases.
The main advantage of a calculator is speed and consistency. It reduces arithmetic mistakes and helps organize the evaluation of metabolic derangement. In many cases, the calculator will also display a corrected result if the serum albumin is low, since hypoalbuminemia can decrease the apparent gap and hide clinically important disease.
A practical workflow is as follows:
- Check the basic metabolic panel or blood gas. Record serum sodium, serum chloride, and bicarbonate. Add albumin if the calculator supports albumin correction. Check the calculated anion gap against the expected reference interval. If the gap is elevated, look for causes of metabolic acidosis. If the result is abnormal, consider whether a mixed acid-base disorder is present.
The calculator is most helpful when paired with the rest of the acid-base picture. A normal number does not automatically mean normal physiology, and an elevated number does not identify the cause by itself. It is a guide for further clinical interpretation, not a final diagnosis.
Anion Gap Formula & Normal Ranges
The classic anion gap formula reads:
Anion gap = sodium - (chloride + bicarbonate)
Some clinicians use potassium in the equation, but many modern calculators exclude it because the effect is small. When potassium is included, the result is slightly higher, https://anion-gap-range805.almoheet-travel.com/anion-gap-calculator-for-isoniazid-toxicity-assessment but the same overall interpretive principles apply.
The normal anion gap varies with the lab method and the reference range used by the laboratory. Different analyzers and measurement techniques can change the expected interval. That is why it is best to interpret the result using the lab’s own reference interval rather than a universal cutoff alone.
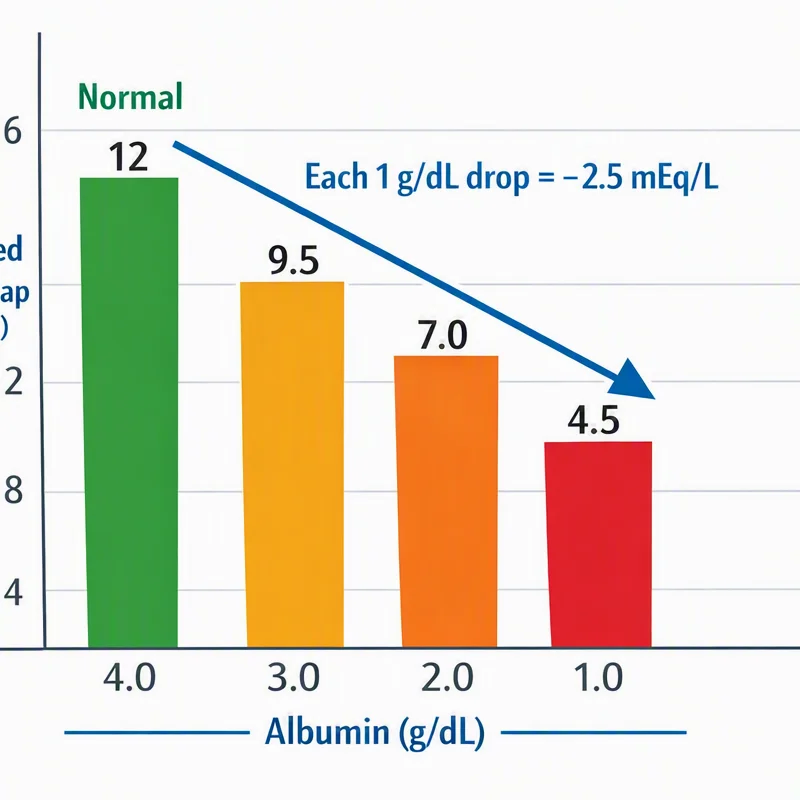
Albumin correction is essential because serum albumin is a major unmeasured anion. When albumin is low, the anion gap may appear falsely normal. Correcting for albumin helps reveal a hidden increase in unmeasured anions. This can be especially important in critically ill patients with metabolic acidosis.
A common clinical approach is to adjust the gap upward when albumin is below normal. The exact correction factor can vary by method, but the principle is the same: low albumin lowers the measured anion difference, so correction improves accuracy. For that reason, a good anion gap calculator often features albumin correction as a built-in feature.
Understanding the formula also helps explain the physiology. The serum contains measured cations and anions, but not all ions are directly measured. The gap represents the difference created by these unmeasured anions, making it a helpful window into hidden metabolic processes.
What delta gap Is and Why It Matters
The delta gap expands the interpretation of the anion gap by comparing the increase in gap to the drop in bicarbonate. This check helps identify whether the patient has only one acid-base problem or a mixed acid-base disorder. It is especially useful in metabolic acidosis when the clinician wants to know if another process is also affecting the bicarbonate level.
This is where the delta-delta ratio is used. The ratio measures the change in anion gap to the change in bicarbonate. If the ratio shows a mismatch, it may indicate an additional disorder such as metabolic alkalosis or another type of metabolic derangement occurring at the same time.
Why does this matter? Because not all cases of acidosis are simple. A patient with high anion gap metabolic acidosis may also have vomiting, diuretic use, or other factors that push bicarbonate in the opposite direction. The delta gap and delta-delta ratio help reveal those overlapping patterns.
In short, the delta gap is a delta calculation that enhances the initial gap calculation. Instead of asking only whether the anion gap is elevated, it asks whether the increase in gap matches the expected drop in bicarbonate. That makes it an useful tool for acid-base interpretation.
Sequential Delta Gap Analysis
To work out the delta gap, at first find the measured anion gap from the chemistry values. Next compare it to the expected anion gap, which is often the upper end of the lab’s normal reference interval. The difference between the measured and expected values is the delta.
Next, compare that delta with the drop in bicarbonate. This comparison can help assess whether the bicarbonate loss is proportional to the increase in unmeasured acids.
A basic approach looks like this:
- Find the measured anion gap. Determine the expected anion gap from the lab reference range. Deduct expected from measured to find the delta gap. Match that value with the change in bicarbonate. Interpret the pattern using the delta-delta ratio.
If the rise in anion gap is larger than the fall in bicarbonate, a second process such as metabolic alkalosis or preexisting elevated bicarbonate may be present. If bicarbonate falls more than expected, another acidifying process may be contributing. Either way, the result supports more nuanced acid-base interpretation.
This step-by-step approach is particularly useful when the clinical picture is unclear. For example, a patient may have metabolic acidosis from one source and vomiting-related alkalosis from another. A basic gap calculation alone may miss that combination, but the delta gap can point toward a mixed acid-base disorder.
How to Read Usual Results
A elevated anion gap metabolic acidosis typically suggests there is excess of acidic compounds or other unmeasured negatively charged ions. The key clinical question is not only whether the gap is elevated, but what is causing the increase and whether compensation is suitable.
In contrast, normal anion gap metabolic acidosis suggests that bicarbonate has been removed and replaced by chloride, so the gap stays within the reference interval. This pattern is frequently described as hyperchloremic acidosis because chloride rises as bicarbonate drops.
Respiratory compensation should also be checked. In metabolic acidosis, the body typically increases ventilation to lower carbon dioxide and partially normalize pH. A blood gas can help determine whether the compensatory response is expected or whether another respiratory disorder is present.
Typical interpretation patterns include:
- High anion gap metabolic acidosis with adequate respiratory compensation. Normal anion gap metabolic acidosis with hyperchloremia and bicarbonate loss. Metabolic acidosis with a superimposed dual acid-base disorder. Elevated gap with atypical bicarbonate behavior suggesting a second process.
In clinical use, clinicians use the anion gap, delta gap, and blood gas in combination. The pattern is more meaningful than any single number. A patient can look physically stable while having a substantial underlying metabolic problem, or appear quite ill with only modest changes in the measured gap.
Origins of Increased Anion Gap
A broadened anion gap suggests presence of unmeasured anions. A number of major conditions can produce this pattern, and the differential diagnosis depends on the general clinical picture, medications, and other lab findings.
Lactic acidosis is a typical cause and may occur with tissue poor perfusion, sepsis, seizures, or severe illness. Elevated lactate adds unmeasured acid to the blood and often causes high anion gap metabolic acidosis.
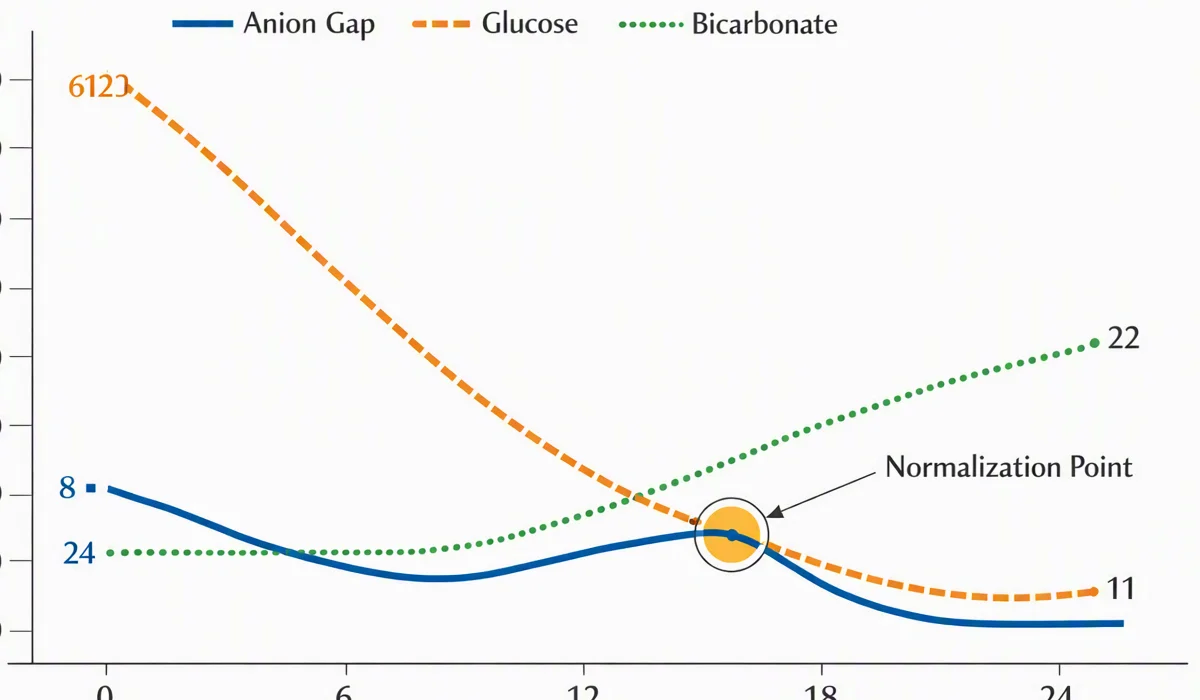
Diabetic ketoacidosis is an additional classic cause. Ketone bodies accumulate and lower bicarbonate while increasing the gap. This is a key example of metabolic derangement where the anion gap calculator can quickly highlight the severity of the acid-base problem.
Renal failure can also increase the anion gap because the kidneys cannot excrete acid effectively. Retained acids and reduced clearance of metabolic byproducts can contribute to the acidotic state.
Toxic alcohols are an significant and potentially dangerous cause. Methanol, ethylene glycol, and similar substances can generate acidic metabolites that increase the gap. In these cases, the gap may be only one clue among many, and urgent clinical assessment is essential.
Other causes may include medications, toxins, and inborn metabolic problems, but the major categories above are the most commonly emphasized. The key point is that an elevated anion gap signals a need to look for hidden acids, not simply to treat the number itself.
Sources of Non-anion Anion Gap Metabolic Acidosis
Regular anion gap metabolic acidosis typically indicates direct depletion of bicarbonate rather than accumulation of unidentified acids. Because the lost bicarbonate is offset by chloride, the serum chloride tends to increase, producing hyperchloremia.
Diarrhea is a classic cause because the gastrointestinal tract can shed large amounts of bicarbonate-rich fluid. This leads to metabolic acidosis with a normal gap and elevated chloride.
Renal tubular acidosis is another significant cause. In this condition, the kidneys fail to handle acid and bicarbonate properly, resulting in persistent acid-base imbalance. Different forms of renal tubular acidosis can have different mechanisms, but they share the pattern of normal gap acidosis.
Bicarbonate loss can also occur through fistulas, certain medications, or renal causes. The common theme is that bicarbonate falls without a corresponding rise in unmeasured anions, so the anion gap may persist within range.
These patterns matter because they affect the workup. If the anion gap is normal, the next question is often whether the problem is gastrointestinal loss, renal tubular disease, or another cause of bicarbonate loss. The chloride level and blood gas results are especially helpful in that analysis.
Constraints and Clinical Caveats
Even a well-designed anion gap calculator has limitations. The biggest one is albumin correction. Because albumin is a important unmeasured anion, low serum levels can hide a true elevation in the gap. Without adjustment, a significant disorder may be missed.
Lab error is another caveat. Sample contamination, analyzer variation, or transcription mistakes can distort the result. If the value does not fit the clinical picture, repeat testing and review of the original basic metabolic panel may be necessary.
The calculated number also indicates the overall acid-base balance at one point in time. It does not reveal how quickly the disorder developed or whether the patient is improving. Serial results can be more informative than a single measurement.
Lastly, clinical context is essential. A mildly abnormal anion gap in a stable patient has a different meaning than the same result in someone with shock, altered mental status, or kidney injury. The calculator helps guide judgment, but it does not replace it.
For best results, assess the anion gap, delta gap, and blood gas together, then compare them with symptoms, medications, and the rest of the chemistry profile. That integrated approach improves the chance of recognizing mixed acid-base disorder and identifying the right underlying cause.
Frequently Asked Questions About Anion Gap and Delta Gap Calculators
What is an anion gap calculator used for?
An anion gap calculator is used to quickly assess metabolic acidosis and identify whether the problem is likely to be a high anion gap metabolic acidosis or a normal anion gap metabolic acidosis. It helps clinicians interpret electrolyte patterns from lab values and decide whether further evaluation is needed.
How is the delta gap determined?
To calculate the delta gap, first find the measured anion gap, then compare it with the expected anion gap from the lab’s reference interval. The difference is compared with the drop in bicarbonate. This helps determine whether there may be a mixed acid-base disorder.
Why can albumin affect the anion gap?
Albumin is a major unmeasured anion, so lower albumin reduces the apparent anion gap. That is why albumin correction matters. Without it, a true gap elevation may be missed, especially in patients with significant illness or low serum albumin.
What is the meaning of a high anion gap mean?
A high anion gap usually means there are additional unmeasured acid substances in the blood, such as those seen in lactic acidosis, diabetic ketoacidosis, renal failure, or toxic alcohols. It typically suggests metabolic acidosis and should be interpreted with the blood gas and overall clinical picture.
Can a normal anion gap still indicate metabolic acidosis?
Yes. Normal anion gap metabolic acidosis is common and often results from diarrhea, renal tubular acidosis, or other causes of bicarbonate loss. In this setting, chloride often rises to maintain electroneutrality, so the gap may remain normal even though the patient is acidotic.