What the Anion Gap Shows
The anion gap is a calculated value that assists clinicians judge an electrolyte imbalance and refine the differential diagnosis of an acid-base disorder. It contrasts major measured serum electrolytes to approximate the amount of unmeasured anions in the blood. In practice, it is a useful clue for finding the cause of metabolic acidosis and interpreting broader acid-base status.
The calculation uses common laboratory values, especially serum sodium, serum chloride, and serum bicarbonate. Because sodium is the primary measured cation and chloride plus bicarbonate are the main measured anions, the difference between them indicates the balance of other charged particles in plasma. A rising anion gap may indicate an acid load from organic acids or toxins, while a normal value can still occur in acid-base problems when bicarbonate is lost and chloride rises to compensate.
Understanding the anion gap is not just about numbers. It is a diagnostic tool that supports clinical interpretation of systemic acid-base problems. The result must be considered alongside the patient’s symptoms, the blood gas, kidney function, and other findings. In other words, the anion gap is most helpful when used as part of a complete review of the clinical picture rather than as a stand-alone answer.
How an Anion Gap Calculator Works
An anion gap calculator streamlines the arithmetic and lowers the chance of calculation mistakes in a high-volume clinical setting. It commonly asks for serum sodium, serum chloride, and serum bicarbonate. Some calculators also accept potassium and albumin, which can increase clinical value in select cases. The calculator then displays the anion gap and may also show a corrected anion gap if albumin adjustment is included.
The core idea is simple: if the measured electrolytes do not fully clarify the patient’s acid-base findings, the calculator helps identify whether there are additional acids present. This is most important in suspected anion gap acidosis, where extra acids consume bicarbonate and leave behind unmeasured anions. Because serum bicarbonate may be low in many forms of acidosis, the calculator helps determine whether the pattern is more consistent with a high-gap process or a non-anion-gap pattern.
Albumin matters because it is a major unmeasured anion. If albumin is low, the anion gap may appear incorrectly normal or only mildly elevated even when clinically meaningful acidosis is present. Some calculators therefore include albumin correction to increase accuracy. This is not a minor detail; it can affect how you interpret a borderline result, especially in patients with chronic illness, poor nutrition, liver disease, or inflammation.
Although potassium is not always included in standard formulas, some clinicians prefer versions that account for it. Potassium contributes to a smaller extent than sodium, chloride, and bicarbonate in most routine calculations, but including it can slightly alter the result. The key is consistency: use the same formula when comparing trends, and interpret changes within the broader diagnostic context.
Anion Gap Formula and Reference Ranges
The standard anion gap formula is:
Anion gap = sodium - (chloride + bicarbonate)
When potassium is factored in, the formula changes to:
Anion gap = sodium + potassium - (chloride + bicarbonate)
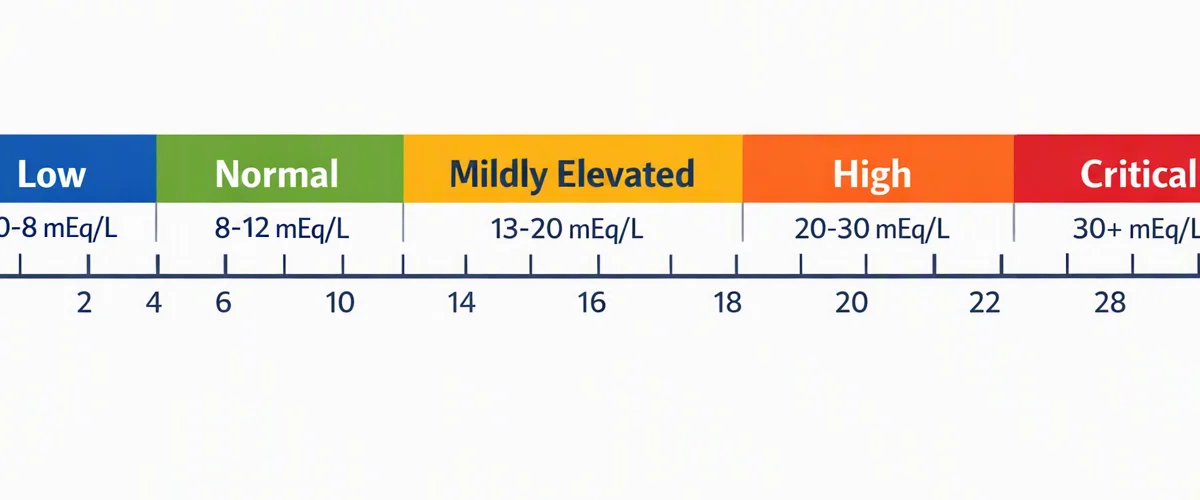
Because multiple laboratories and calculators may use varying conventions, the reference range can change. That variability is one reason a reported result should consistently be interpreted in light of the specific laboratory method and the patient’s overall condition. A “normal” result on one system may differ slightly from another, so the normal anion gap is best understood as a method-dependent range rather than a one universal number.
Most clinicians focus on whether the anion gap is high, normal, or low compared with the expected reference range. A elevated gap often points toward accumulation of unmeasured acids. A normal value does not exclude acidosis, because many acid-base disorders lower bicarbonate while increasing chloride enough to keep the gap unchanged. That pattern is central to recognizing normal anion gap metabolic acidosis.
Albumin correction should be taken into account when albumin is abnormal, especially if the value is low. Since albumin is a major contributor to the gap, low albumin can mask a clinically significant acid burden. In practice, the corrected result may reveal a more accurate picture of the patient’s true acid-base status and avoid missed recognition of a high-gap process.
High Anion Gap Acid-Base Disorder Causes
This acid-base disorder happens when acids accumulate and consume bicarbonate, leaving unmeasured anions remaining. This is a frequent form of systemic acidemia and often indicates a major underlying problem that requires prompt assessment. The major causes include lactic acidosis, ketoacidosis, and uremia, among others.
Lactate accumulation occurs when lactate production exceeds clearance, often in settings of tissue hypoperfusion, severe infection, seizures, hypoxemia, or impaired metabolism. Because lactate is an unmeasured anion, its buildup raises the anion gap and contributes to systemic acidemia. In such cases, the calculator result can reinforce the suspicion of shock, poor perfusion, or another major physiologic stressor.
Ketone accumulation develops when ketone production rises substantially, as in diabetic ketoacidosis, alcoholic ketoacidosis, or starvation states. Ketones act as unmeasured acids and widen the gap. Here, the anion gap calculator can be helpful for trend monitoring, helping clinicians assess whether treatment is narrowing the gap as the metabolic derangement resolves.
Advanced kidney dysfunction from advanced kidney dysfunction is another classic cause. With decreased renal clearance, acids are not excreted normally, and retained organic acids contribute to the elevated gap. The result may reflect both reduced clearance of acids and accumulation of other metabolites. In this setting, the calculator assists with recognition of kidney-related acid retention, https://anion-gap-analyzer309.tearosediner.net/what-is-the-meaning-of-an-anion-gap-of-20-mean but it should always be paired with renal studies and the clinical presentation.
Normal Anion Gap Metabolic Acidosis Reasons
Normal anion gap metabolic acidosis is commonly referred to as hyperchloremic acidosis because chloride rises as bicarbonate falls, preserving the calculated gap. This pattern can be just as clinically important as a high-gap disorder, even though the calculator does not show an elevated value. The main concept is loss of bicarbonate or failure to regenerate bicarbonate, rather than accumulation of unmeasured acids.
Diarrhea is a frequent cause because the gastrointestinal tract can lose large amounts of bicarbonate-rich fluid. As bicarbonate drops, the body retains chloride to maintain electroneutrality, and the gap remains in the normal range. This is a classic example of why a normal result does not rule out acidosis.
Renal tubular acidosis is another significant cause. In this disorder, the kidneys fail to properly handle acid excretion or bicarbonate conservation, leading to persistent metabolic acidosis with a normal gap. The patient may have a mildly subtle presentation, which makes laboratory pattern recognition essential. An anion gap calculator helps separate this from high-gap conditions that require different urgent responses.
Other causes also match this pattern, but the central concept is the same: loss of bicarbonate or impaired acid handling without major accumulation of unmeasured anions. Recognizing this helps avoid mislabeling the disorder and supports a more accurate differential diagnosis.
Interpreting Values in Clinical Practice
The anion gap should not ever be interpreted in a vacuum. A useful assessment includes the blood gas, pH, serum chloride, bicarbonate, and the broader clinical picture. A low bicarbonate alone does not differentiate between high-gap and normal-gap acidosis. The pH tells you whether the patient has systemic acidemia, while the anion gap helps explain the likely mechanism.
If the blood gas shows acidemia and the anion gap is elevated, the pattern is consistent with a high-gap process such as lactic acidosis, ketoacidosis, or uremia. If the pH is low but the gap is normal, evaluate for diarrhea, renal tubular acidosis, or another hyperchloremic process. The serum chloride is very helpful here because a rise in serum chloride often accompanies loss of bicarbonate in normal-gap states.
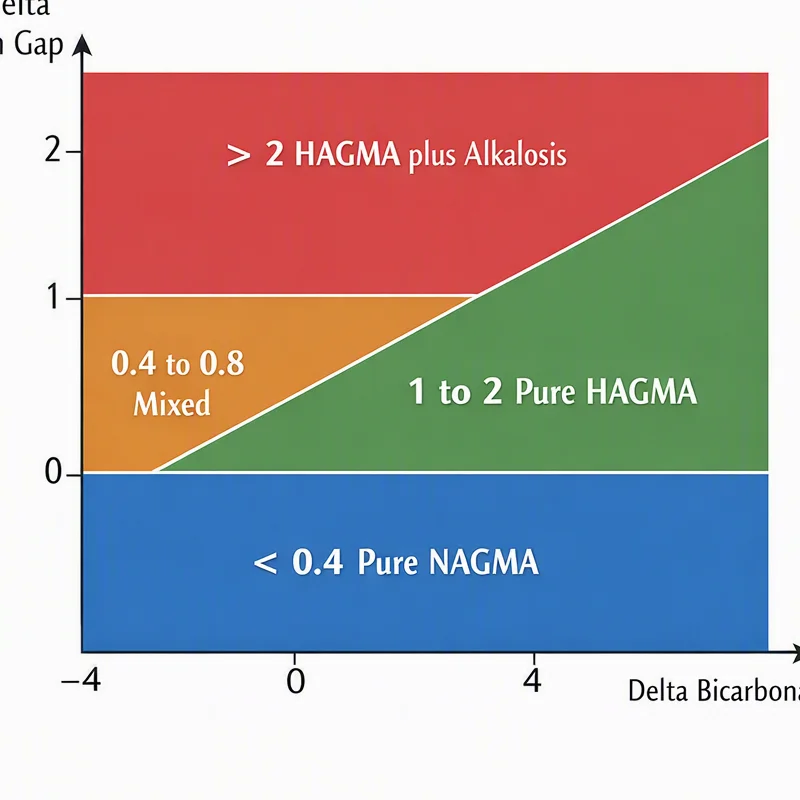
The delta gap can help detect a mixed acid-base disorder. This approach compares the rise in anion gap to the fall in bicarbonate. If the gap increase is much larger or smaller than expected, another acid-base process may be present at the same time. For example, a patient may have a high-gap acidosis plus a metabolic alkalosis, or a high-gap acidosis plus an additional normal-gap component. That is why the calculator result should be viewed in interpretive context rather than as a simple yes-or-no answer.
In practice, the best use of the calculator is pattern recognition. Ask whether the result fits the blood gas, the clinical scenario, and the likely source of the acid-base problem. This approach improves diagnostic accuracy and helps inform timely next steps.
Common Mistakes and Constraints
A number of factors can affect interpretation. Hypoalbuminemia is one of the key because it lowers the measured gap and can hide a medically important high-gap process. If there is no albumin correction, a patient with true acid burden may appear to have a near-normal result. This is a frequent reason for minimizing the severity of acidosis.
Laboratory error is another problem. A single abnormal value may suggest sample handling problems, contamination, or an analytic problem rather than true physiology. When the number does not fit the clinical picture, repeat testing and review of the specimen and methods may be required. Because the anion gap is derived from other values, an error in sodium, chloride, or bicarbonate can shift the final result significantly.
Measurement variability across laboratories can also affect the reference range and the interpretation of borderline cases. Different analyzers may report slightly different values, especially for bicarbonate or chloride. In addition, a mixed acid-base disorder can partially counterbalance the expected pattern and make the gap appear less obvious than it truly is. These limitations do not lessen the usefulness of the calculator, but they do reinforce the need for careful clinical interpretation.
Finally, a normal result does not eliminate disease. The calculator is best used as a structured tool to spot likely patterns, not as a substitute for the full clinical assessment. That is especially true when the patient has complex illness, fluctuating renal function, or multiple simultaneous metabolic derangements.
When to Seek Immediate Medical Attention
Acidosis can become dangerous rapidly, particularly when it is severe or accompanied by worsening symptoms. Get prompt medical attention if there are signs of severe acidosis or an abrupt decline in condition. Worrisome symptoms may include deep or rapid breathing, profound weakness, vomiting, chest discomfort, marked fatigue, or inability to stay awake.
Confusion is particularly important because it may signal worsening acidemia, poor perfusion, infection, toxic exposure, or another serious cause of metabolic derangement. Respiratory distress is also a red flag, since the body may be trying to compensate for acidosis by increasing ventilation. If breathing becomes labored, the patient is not compensating adequately or the underlying problem may be advancing.
An anion gap calculator can help spot a worrisome pattern, but it should not delay care when the patient appears unstable. If the lab pattern and clinical presentation suggest severe illness, urgent evaluation is appropriate even before all confirmatory testing is complete.
FAQ
What is an anion gap calculator used for?
An anion gap calculator is used to determine the anion gap from common serum electrolytes and help evaluate the cause of acidosis. It supports recognition of high anion gap metabolic acidosis, normal anion gap metabolic acidosis, and possible mixed disorders. It is a practical diagnostic tool for clinical interpretation, especially when paired with blood gas results and other laboratory values.
What does a high anion gap mean in acidosis?
A high anion gap in acidosis usually means there are extra unmeasured acids in the blood. Common causes include lactic acidosis, ketoacidosis, and uremia. In this setting, the calculator suggests that bicarbonate has been consumed by acid load, which helps narrow the differential diagnosis and identify the likely source of the metabolic acidosis.
How do you calculate the anion gap for albumin?
Correcting for albumin raises the anion gap higher when albumin is low, because albumin is a major unmeasured anion. The precise correction method can change by formula, but the basic idea is to estimate the hidden contribution of low albumin so the corrected anion gap better reflects true acid-base status. This is especially useful when hypoalbuminemia may mask a increased-gap disorder.
What causes a normal anion gap metabolic acidosis?
Normal anion gap metabolic acidosis is often caused by diarrhea, renal tubular acidosis, and other forms of bicarbonate loss or impaired bicarbonate handling. In these cases, chloride tends to rise as bicarbonate falls, so the gap remains within the reference range even though acidosis is present. That is why a normal result does not eliminate clinically important acid-base disease.
Can the anion gap be normal even when acidosis is present?
Yes. Acidosis can be present with a normal anion gap, especially in normal anion gap metabolic acidosis due to diarrhea or renal tubular acidosis. This is why the anion gap calculator should be interpreted alongside pH, blood gas findings, serum chloride, and the overall clinical picture. Albumin correction may also expose a hidden high-gap process when the uncorrected value appears normal.