How is defined the anion gap?
The anion gap is a computed value used to help interpretation of acid-base balance and identify causes of metabolic acidosis. It is based on common electrolytes measured in blood, especially sodium, chloride, and bicarbonate. Clinicians rely on it as a fast clue that there may be excess acids in the blood or that important ions are absent from the standard measurement.
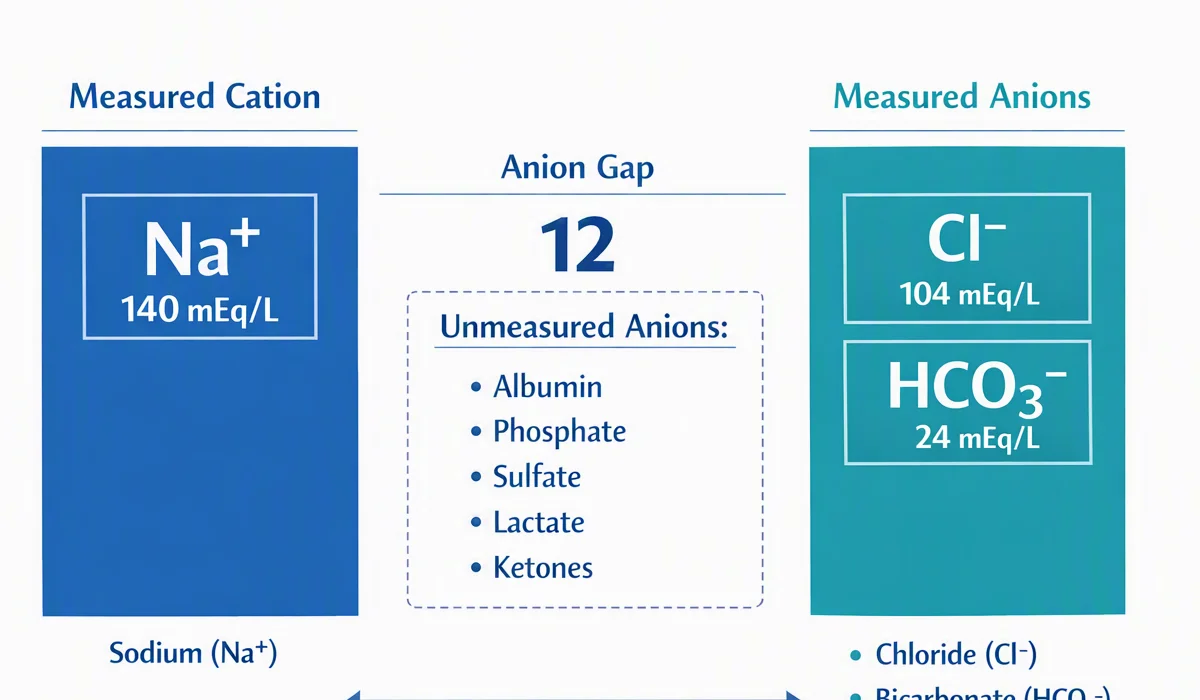
In simple terms, the anion gap compares the positively charged and negatively charged particles in the bloodstream. Because not all ions are directly measured on routine labs, the result can indicate the presence of unmeasured anions. This makes it a valuable biochemical marker in the evaluation of acid-base disorders.
The anion gap is often checked alongside the rest of the serum chemistry or electrolyte panel. A change in the gap does not diagnose a disease by itself, but it can lead to a diagnostic workup that looks for organic acids, kidney problems, toxins, or tissue hypoperfusion. In that sense, the anion gap is a practical tool for clinical interpretation rather than a stand-alone diagnosis.
In what way an Anion Gap Calculator works
An Anion Gap Calculator uses values from a basic metabolic panel or similar lab report to determine the gap. Typical calculators use sodium, chloride, and blood bicarbonate, https://anion-gap-help700.nexorafield.com/posts/the-importance-of-albumin-correction-matters-in-anion-gap-interpretation then follow a standard formula. The specific equation may vary slightly depending on whether potassium is included, but the most common approach is simple and fast.
Because the calculation is easy, the result can be generated quickly from routine laboratory data. That makes the calculator helpful when a clinician wants to check for an acid-base disorder or confirm a suspicious test result. It can also be useful for patients trying to make sense of what a lab report may mean, especially when the result is unexpectedly high or low.
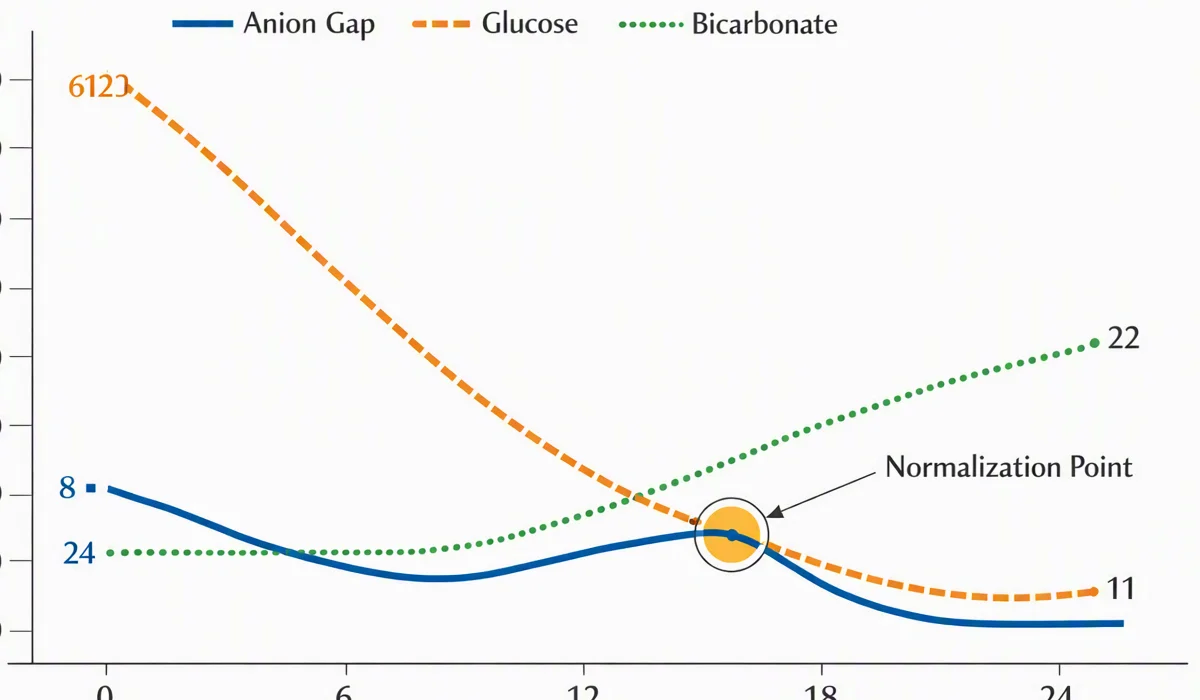
However, the calculator only works well when the input values are read in context. The anion gap is affected by albumin, the main negatively charged protein in blood, and by shifts in acid-base balance that may not be obvious from the basic numbers alone. A calculator can identify a important threshold, but it cannot explain the cause on its own.
For that reason, the most effective use of an Anion Gap Calculator is as part of a wider assessment that includes symptoms, other labs, and the overall clinical picture. If the calculator suggests an abnormal result, the next step is usually a careful review of bicarbonate, kidney function, lactate, and albumin to decide whether the finding reflects a true acid-base problem or a corrected value that changes the interpretation.
Can severe liver dysfunction raise the anion gap?
Absolutely, severe liver dysfunction can increase this gap, but not in each situation. This link usually comes from the way severe impaired liver function affects acid metabolism, body chemistry, and the body’s ability to remove acids from the blood. When the liver is failing, lactate buildup is one of the main reasons the gap may go up.
The liver normally helps metabolize blood lactate, so when liver function is reduced, lactate can build up. This can lead to elevated anion gap acidosis, especially if the person is also critically ill or has reduced blood flow. In other words, liver failure does not automatically cause a high anion gap directly, but it can make an elevated gap more likely by impairing acid clearance and leading to metabolic derangement.
Severe liver disease may also coexist with other causes of acidosis, including an infection, low blood pressure, or kidney injury. In that setting, the anion gap becomes a helpful sign rather than a final answer. A high gap should prompt a search for the complete cause, not just the liver problem alone.
In liver failure, a high anion gap often reflects the combined impact of impaired metabolism, elevated lactate, and other systemic stressors rather than one single mechanism.
Reasons why liver failure may affect acid-base balance
The liver acts a major role in acid-base balance. When it is operating normally, it promotes metabolism, works to clear acids, and contributes to steady blood chemistry. In liver failure, those functions weaken, which can shift the body toward metabolic acidosis or additional acid-base disturbances.
One major issue is reduced lactate clearance. Lactate is produced in many tissues, especially during low oxygen states, and the liver helps remove it from circulation. If hepatic clearance drops, lactate may rise and contribute to a high anion gap. This is especially important in critical illness, when oxygen delivery is already compromised.
Another factor is sepsis, which is common in advanced liver disease and can trigger tissue hypoperfusion. When tissues do not receive enough blood flow, they generate more lactate and other organic acids. These acids are organic acids that can increase the anion gap and worsen the acid-base disturbance.
Renal dysfunction can also occur alongside hepatic failure. If the kidneys cannot excrete acids normally, the body accumulates more unmeasured anions. This can magnify the rise in the anion gap and make the lab pattern look more severe than liver disease alone would suggest.
Other reasons of an elevated anion gap in liver disease
In cases of liver disease and an elevated anion gap, it is important not to assume the liver is the only factor. Many other problems can coexist and elevate the gap, especially in the setting of advanced illness. A detailed diagnostic workup should consider the most common confounders.
Ketosis is one significant possibility. People with limited intake, alcohol use disorder, or diabetes may develop ketone buildup that increases the anion gap. In liver disease, this may happen more easily because illness can disrupt normal metabolism and reduce energy intake. Ketones are unmeasured anions, so they can significantly affect the calculation.
Toxins are another concern. Certain ingestions can cause a high anion gap metabolic acidosis, and the presence of hepatic dysfunction may make interpretation more challenging. The liver normally helps metabolize or process many substances, so toxin-related acid-base disorders can be harder to clear when liver function is poor.
Renal failure can also elevate the gap by preventing acid excretion and allowing acids to accumulate. If liver disease and renal failure occur together, the lab pattern may reflect combined organ dysfunction rather than a single source. This overlap is typical in serious systemic illness.
Reduced albumin is especially important in chronic liver disease. Low albumin can lower the apparent anion gap and make a true abnormality easier to miss. That means a patient with liver disease may have an elevated gap that seems only slightly abnormal, even when the underlying acid burden is significant.
How serum albumin influences anion gap results reading
Albumin levels is a major determinant to the measured anion gap because it has a negative charge. With low albumin, the anion gap may seem lower than expected even if extra acids are present. That is why albumin correction matters so much in liver disease, where hypoalbuminemia is common.
In the absence of correction, the raw number can lead to misleading conclusions. A patient with low albumin may look “normal” on paper even though the actual acid burden is elevated. This is why, clinicians often calculate a corrected anion gap to estimate the more accurate value. The corrected value helps account for the loss of negatively charged proteins and improves clinical interpretation.
Albumin binding also helps explain the effect. Albumin contributes to the body’s buffering capacity, so as albumin decreases, the chemical balance changes. The calculator result may therefore understate the true problem unless the albumin level is reviewed at the same time.
In practical terms, an Anion Gap Calculator is most useful when paired with albumin. With low albumin, the raw gap should be interpreted cautiously. In liver disease, this step is often essential because hypoalbuminemia is common and can mask a clinically important acid-base disorder.
When a elevated anion gap requires prompt evaluation
A high anion gap is not always an urgent situation, but it can be a indicator of a critical acid-base disorder. In someone with liver failure, immediate evaluation is especially important if the lab change comes with symptoms such as disorientation, severe weakness, breathing quickly, vomiting, chest pain, fainting, or marked drowsiness. These emergency symptoms may indicate progressive acidosis or some other dangerous process.
Testing often includes a blood gas to determine whether the body is acidotic and how severe the disturbance is. A blood gas can help confirm whether the change is primarily metabolic, respiratory, or mixed. It also helps clinicians understand whether the lungs are compensating for the underlying issue.

Because the anion gap is tied to the full electrolyte pattern, a significant abnormality may signal a broader electrolyte imbalance that needs immediate attention. In liver disease, that imbalance might reflect lactate buildup, kidney injury, infection, toxin exposure, or a different systemic illness.
Seek prompt care if a high anion gap appears with worsening jaundice, severe abdominal pain, dehydration, low blood pressure, or a sudden change in mental status. These findings can indicate a critical metabolic problem that needs prompt evaluation rather than watchful waiting.
Commonly asked Q&As
Could liver failure immediately cause a high anion gap?
Liver failure can contribute to a high anion gap, but it typically does so in an indirect way. The main mechanism is impaired lactate clearance, which can result in lactic acidosis and high anion gap metabolic acidosis. Other issues like infection, kidney injury, or poor tissue perfusion often play a role too.
How does low albumin change the anion gap?
Low albumin decreases the number of negatively charged proteins in the blood, which can make the measured anion gap seem reduced than it really is. This is why albumin correction is important in liver disease and why a corrected anion gap can be more accurate than the raw number.
What is the normal anion gap range?
The anion gap normal range can vary a bit depending on the laboratory method and whether potassium is included in the formula. Many labs set the usual range to be roughly in the low-to-mid teens or slightly lower. Because ranges are not identical, the lab’s reference interval should always guide diagnosis.
Is a high anion gap always be an emergency in liver disease?
Not always, but it should never be ignored. A high gap may suggest a mild or temporary shift, but in liver disease it can also signal severe metabolic acidosis, sepsis, renal dysfunction, or toxin exposure. If symptoms are present, or if the number is significantly abnormal, urgent evaluation is warranted.
Which tests are used to find the cause of a high anion gap?
Common tests include repeat electrolytes, a basic metabolic panel, serum bicarbonate, lactate, kidney function tests, ketone testing, and a blood gas. Depending on the situation, clinicians may also check for toxins, infection, or other causes of acid buildup. These tests help connect the anion gap to the underlying metabolic derangement and guide treatment.