What the Anion Gap Measures
The anion gap is a practical way to look at acid-base balance through standard blood chemistry. It helps estimate the relationship between positively charged ions and negatively charged ions in the blood, particularly when reviewing serum sodium, serum chloride, and serum bicarbonate. Because many important ions are not directly measured on a standard panel, the anion gap acts as a valuable window into unmeasured anions and, indirectly, unmeasured cations.
In simple terms, the anion gap reflects electroneutrality, the principle that blood must remain electrically balanced. When the measured values from a basic metabolic panel are compared, the result can signal whether there is an acid-base disorder such as metabolic acidosis. That is why the anion gap is such a important diagnostic tool in everyday lab interpretation.
The calculation does not identify a disease by itself. Instead, it helps organize the differential diagnosis and place a laboratory result into clinical context. A normal value can be reassuring, but it does not always exclude a serious problem. Likewise, an abnormal value should be interpreted with the rest of the serum electrolytes, the patient’s symptoms, and any relevant history of illness or medication exposure.
How an Anion Gap Calculator Works
An anion gap calculator employs a simple formula to the results in a typical electrolyte panel. The usual version uses sodium, chloride, and bicarbonate to determine the gap between measured cations and anions. Because these are common components of a basic metabolic panel, the calculation is simple to perform and often appears automatically in laboratory results.
Although the exact formula can change by laboratory, the classic approach is:
Anion gap = serum sodium - (serum chloride + serum bicarbonate)
Some labs use slightly different methods or include potassium in special cases, but the core idea stays the same. The calculator is not measuring a single substance. Instead, it is a mathematical shortcut that estimates how much “gap” exists after the measured serum electrolytes are included. That gap reflects the presence of acids, proteins, or other ions not directly detected by routine testing.
Used well, the calculator supports a more comprehensive diagnostic evaluation. It helps clinicians assess whether the pattern looks like high anion gap metabolic acidosis, a normal anion gap process, or a low anion gap pattern that may indicate another issue. The value should under no circumstances be interpreted in isolation; it is one part of a larger blood chemistry assessment.
Typical Limits and Reference Ranges
The usual anion gap is not the same across all lab. A given reference range may differ depending on the analyzer, calibration method, and whether potassium is included. This is why laboratory variation is so important in lab interpretation. A result that looks slightly high in one setting may still remain within expected limits in another.
Albumin also influences the expected range. Since albumin is a negatively charged protein, lower levels can lower the measured anion gap even when the underlying acid-base state is abnormal. For that reason, a “normal” result can sometimes be misleading if hypoalbuminemia is present.
As a practical rule, check the result with the specific lab’s printed reference interval rather than basing it on a single universal number. Review whether the test was drawn as part of a basic metabolic panel or a broader electrolyte panel, and review whether other values suggest an electrolyte imbalance or a broader metabolic disturbance. The reference range is a guide, not an endpoint.
Reading High Anion Gap
A raised anion gap metabolic acidosis generally suggests there are extra acids in the blood or a rise of unmeasured anions. This pattern deserves attention because it may signal an serious acidotic state. This finding is commonly accompanied by low bicarbonate and may be accompanied by clinical findings such as rapid breathing, confusion, nausea, or weakness.
Frequent causes include lactic acid buildup, ketone-related acidosis, renal failure, uremic syndrome, toxic alcohol ingestion, and salicylate toxicity. Each cause has its own clinical pattern. For example, lactic acidosis can occur with tissue hypoperfusion or severe infection, while ketoacidosis is often associated with insulin deficiency or prolonged fasting. Toxic exposures should be considered when the presentation is sudden, severe, or unexplained.
In practice, a high result from an anion gap calculator should lead you to look for the underlying cause rather than a focus on the number alone. Review the full clinical picture, including medications, kidney function, glucose, lactate, and ketone status. If the elevation is marked, the pattern may represent a significant acid base disorder that requires prompt attention.
Explaining a Typical or Decreased Anion Gap
A normal anion gap metabolic acidosis can arise when bicarbonate is lost but the gap does not change because chloride rises to compensate. This pattern is sometimes called hyperchloremic metabolic acidosis. It often points toward gastrointestinal bicarbonate loss, certain kidney problems, or other causes of non-gap acidosis. The key is to understand that a normal gap does not mean no acidosis is present.
A low anion gap is less common and is often overlooked. One of the most frequent explanations is decreased albumin, because reduced albumin lowers the expected gap. Another important consideration is plasma cell myeloma, where abnormal proteins can alter the balance of charged particles in blood. Laboratory artifact, medication effects, or unusual ion patterns can also be involved.
When the result is unexpectedly low, run again the analysis if needed and review the entire blood chemistry profile. A low value can be a clue to an underlying disease, but it may also reflect a technical issue or an unrecognized shift in electrolyte levels. The safest approach is to interpret it alongside the rest of the data and the patient’s symptoms.
Albumin Correction and Its Clinical Significance
The corrected anion gap accounts for the effect of albumin on the measured result. Because albumin is one of the major unmeasured anions, low concentrations can mask a true acid-base disorder. For this reason albumin correction is so important when the measured gap appears normal or only mildly abnormal.
In general, a decreased serum albumin means the expected gap should be raised accordingly. The exact adjustment may vary by institution, but the purpose is the same: to avoid missing metabolic acidosis that is being masked by hypoalbuminemia. If the corrected value is elevated, the patient may actually have a high anion gap metabolic acidosis despite a deceptively ordinary initial number.
Applying the corrected value improves anion gap correction and helps align the lab finding with the patient’s physiology. This step is especially helpful in critically ill patients, those with chronic illness, or anyone whose albumin is known to be low. In other words, correction makes the diagnostic tool more accurate in real-world clinical context.
Frequent Causes and Medical Context
The clearest assessment comes from linking the number with the likely reason. Renal failure can increase the gap because acids are not cleared and uremia adds to the accumulation of unmeasured materials. Sepsis may drive lactate production and lead to lactic acidosis. Ketoacidosis may arise in diabetes, alcohol use, or prolonged starvation. These findings all represent different forms of metabolic disturbance, but they can coexist on a laboratory panel.
Salicylate toxicity and toxic alcohols are especially critical not to miss because they can cause severe abnormalities and need urgent treatment. The anion gap does not reveal the toxin, but it can raise suspicion early. In a patient with altered mental status, unexplained acidosis, or a sudden change in the electrolyte profile, these causes should move high on the list.
Clinical setting matters because the same laboratory result can signify different things in different patients. For example, a modest elevation in a stable outpatient may warrant a different response than a similar value in a critically ill patient with worsening acid-base balance. The calculator is best used as part of a broader diagnostic evaluation, not as a isolated answer.
Step-by-Step Interpretation Workflow
A careful workflow makes anion gap interpretation more uniform and less prone to skip significant findings. Begin with the electrolyte panel and check the sodium, chloride, and bicarbonate values used in the calculation. Next compare the result with the lab’s reference range. Then decide whether the pattern suggests a normal anion gap, a high anion gap metabolic acidosis, or a low anion gap.
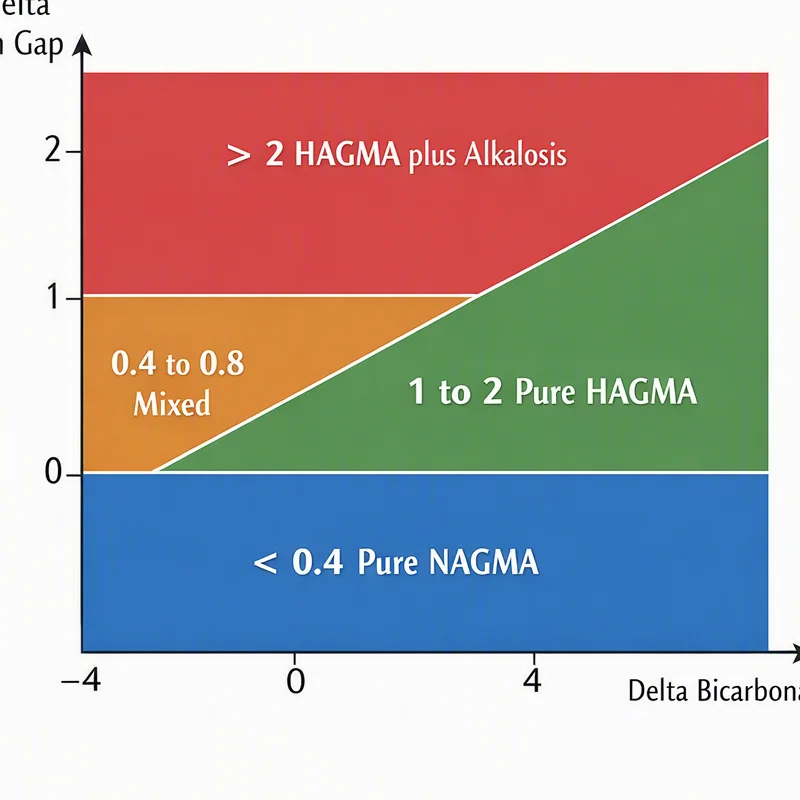
Next, assess acid-base status with a blood gas if available. The blood gas aids confirm whether there is true acidemia or alkalemia and can resolve mixed disorders. If the anion gap is elevated, consider the delta gap to detect additional acid-base processes. This step is especially useful when the bicarbonate drop does not match the degree of gap elevation.
A simple sequence is:
- Assess the serum sodium, serum chloride, and serum bicarbonate. Confirm the reported result from the anion gap calculator. Review albumin abnormalities and use corrected anion gap interpretation. Assess for clues to lactic acidosis, ketoacidosis, renal failure, or toxin exposure. Apply the delta gap when mixed disorders are possible. Integrate the result with the patient’s symptoms and overall clinical context.
This systematic method supports better lab interpretation and avoids overreaction to a single laboratory result. It also renders the process easier to repeat when serial https://anion-gap-estimator988.timeforchangecounselling.com/what-is-an-anion-gap-calculator-used-to-do labs are collected.
When to Pursue More Evaluation
Additional assessment is appropriate when the result is far outside the expected range, when there is a sudden change from prior testing, or when the pattern does not fit the clinical picture. Critical values should be treated seriously, especially if the patient has concerning clinical symptoms such as shortness of breath, chest pain, confusion, vomiting, or reduced level of consciousness.
If the result appears inconsistent with the patient’s condition, a repeat test can help confirm whether the value is genuine or due to sample processing, collection timing, or analyzer variation. Sometimes, a confirmatory arterial blood gas is necessary to more clearly assess acid-base status. This is especially relevant when there is suspected metabolic acidosis or a mixed disorder that calls for close observation.
Seek prompt reassessment when the anion gap is abnormal and the patient has increasing symptoms, suspected poisoning, signs of shock, or kidney dysfunction. A calculator is a useful starting point, but it does not take the place of careful medical review, repeat measurement, or broader diagnostic evaluation when the situation is unstable.
Frequently Asked Questions
What is an anion gap calculator used for?
An anion gap calculator is used to interpret routine blood chemistry and help identify patterns of metabolic acidosis. It uses the values from a basic metabolic panel or electrolyte panel to assess whether there are extra unmeasured acids or other abnormalities affecting acid-base balance. It is a useful diagnostic tool for lab interpretation.
What does a high anion gap mean?
A high result often indicates high anion gap metabolic acidosis, which can be caused by lactic acidosis, ketoacidosis, renal failure, uremia, toxic alcohols, or salicylate toxicity. The meaning depends on the patient’s clinical context, symptoms, and other lab findings.
Can low albumin affect the anion gap?
Yes. Albumin is a major unmeasured anion, so hypoalbuminemia can decrease the measured anion gap. That is why corrected anion gap interpretation and albumin correction are important when the value seems unexpectedly normal or low.
What is the typical anion gap range?
The expected anion gap varies by the lab’s reference range and the testing method. Because of laboratory variation, the best method is to use the range reported with the test result. Always assess it together with blood electrolytes and the rest of the chemistry panel.
When should an abnormal anion gap be evaluated further?
An abnormal result should be investigated further when it is a critical result, when it does not match the patient’s symptoms, or when there is concern for a significant illness such as acidosis, poisoning, kidney dysfunction, or sepsis. A repeat test, a blood gas or arterial gas, and review of the delta-delta gap may be needed to help identify the acid-base disorder.