What Is the Anion Gap and Why Does It Count in Shock?
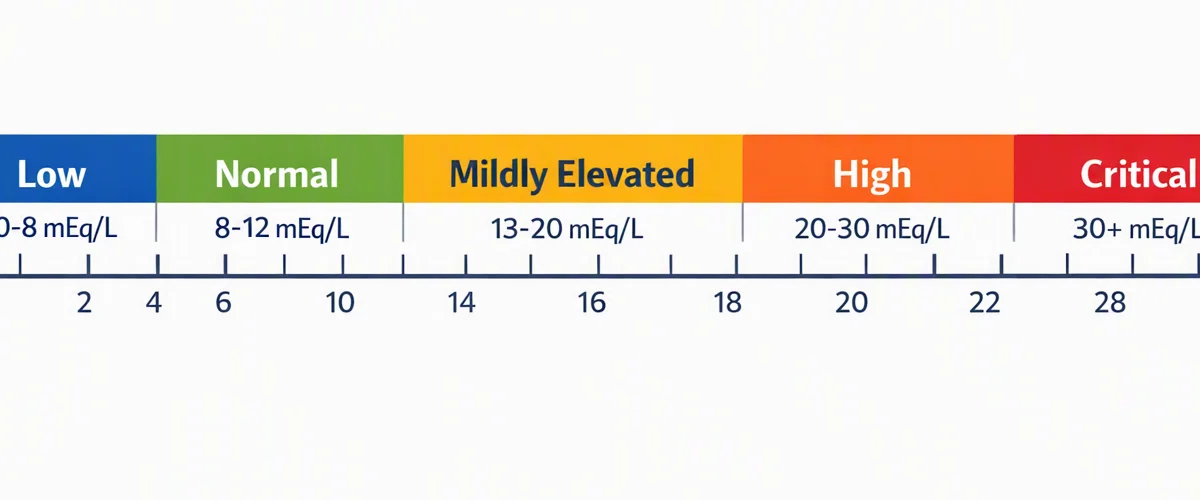
The anion gap is a useful way to search for hidden acids in the blood and to distinguish causes of metabolic acidosis during shock. In clinical practice, it is part of a broader acid-base interpretation that starts with the electrolytes in a standard serum chemistry panel. When tissue oxygen delivery drops, the body may shift toward anaerobic pathways and produce acid, making the anion gap a useful diagnostic clue in undifferentiated shock.
In shock, the anion gap is important because it can point toward a perfusion problem, a toxic exposure, or another secondary cause of metabolic derangement. A rising gap often suggests unmeasured anions are accumulating, while a normal gap may indicate bicarbonate loss or a different acid-base disorder. Either way, the number should be interpreted in the context of hemodynamic instability, resuscitation status, and the rest of the clinical assessment.
A useful way to think about the anion gap is as a diagnostic marker that narrows the differential. It does not diagnose shock by itself, but it can help identify whether the acid-base disorder is more consistent with lactic acidosis, ketoacidosis, renal failure, toxic alcohols, or another process. In critical care, that distinction can change the next step quickly.
How to Apply an Anion Gap Calculator Accurately
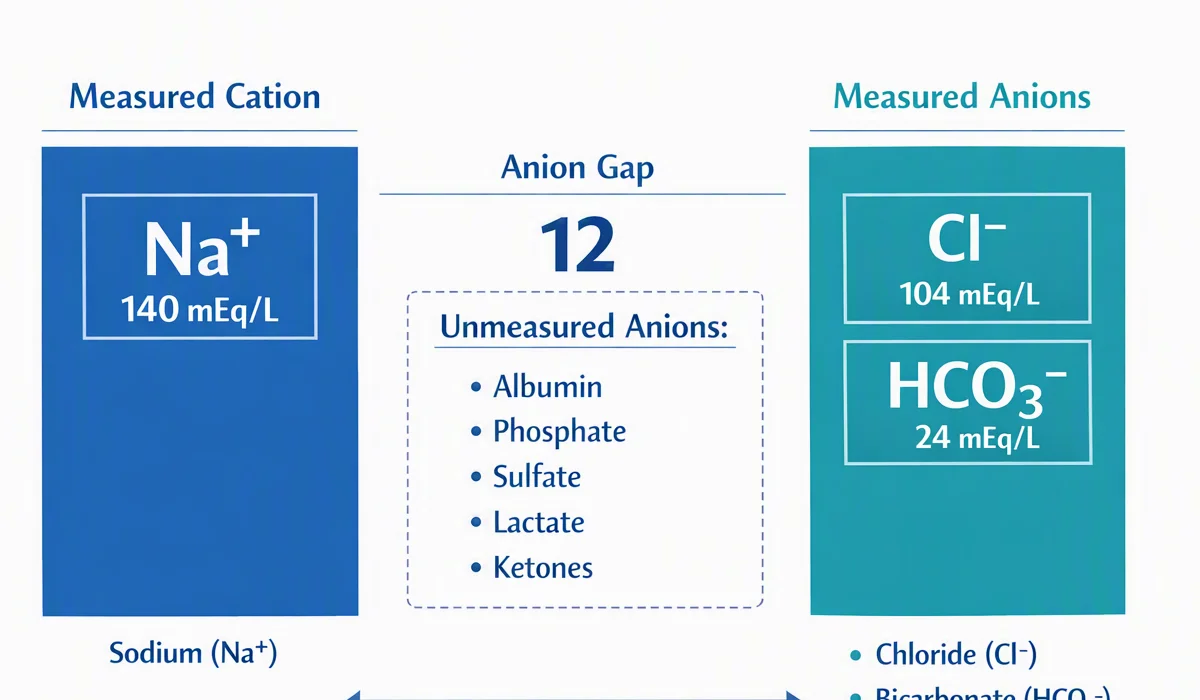
An anion gap calculator is only as reliable as the values entered into it. The computation usually depends on serum sodium, serum chloride, and serum bicarbonate, which are obtained from the electrolyte panel. Because the output can influence urgent decisions, the numbers should be checked for alignment with the broader serum chemistry and the clinical picture.
Most calculators use a standard formula that compares measured cations and anions. If the result seems unusual, first verify the lab values and confirm whether the bicarbonate is from the chemistry panel rather than a blood gas. Even small changes in chloride or bicarbonate can alter interpretation, especially in a patient with evolving shock and ongoing resuscitation.
To use the calculator correctly, consider these steps:
- Confirm the electrolyte panel is current and not outdated. Use the identical set of values from one blood draw when possible. Check whether albumin is reduced, since that can mask a real gap. Compare the result with the arterial blood gas and lactate. Interpret the number as part of acid-base analysis, not in isolation.
The anion gap calculator is especially helpful when the clinical question is whether the patient’s acidosis suggests unmeasured acids or another pattern. In shock, this can strengthen rapid bedside reasoning, but it should never replace clinical assessment or trend monitoring.
What Does a High Anion Gap Suggest in Shock?
A high anion gap in shock usually suggests accumulation of acids or toxins. The most common cause in unstable patients is lactic acidosis, which often signals tissue hypoperfusion. When blood flow and oxygen delivery are inadequate, cells shift to anaerobic metabolism, generating lactate and raising the gap upward.
This pattern is common in sepsis, hemorrhage, cardiogenic shock, and other states with impaired perfusion. The anion gap becomes a valuable diagnostic clue because it may rise before the clinical picture fully emerges. In a patient with metabolic acidosis and hemodynamic instability, a high gap should raise concern for ongoing oxygen debt and inadequate resuscitation.
That said, a high anion gap does not automatically mean the cause is lactate. It only indicates that unmeasured acids are present. The next step is to match the lab pattern with the story: infection, hypoperfusion, renal dysfunction, diabetic decompensation, or ingestion. In critical care, the value is strongest when combined with the arterial blood gas, lactate, and bedside findings.
In shock, a rising anion gap often signals worsening perfusion deficit, but the cause still needs targeted identification.
How Do You Differentiate Causes of High Anion Gap Acidosis?
When a high gap is detected, the main goal is to determine the underlying secondary cause. In shock, the main possibilities are ketoacidosis, renal failure, toxic alcohol ingestion, and salicylates. Each has a different treatment pathway, so the pattern on the labs and the history are important.
Ketoacidosis may be seen in diabetes, starvation, or alcohol-related states and often presents with an elevated gap plus low serum bicarbonate. Renal insufficiency can also produce a high gap because acid clearance is impaired. With toxic alcohol exposure, the gap may be high early, sometimes before an osmolar gap closes in, and the patient may have neurologic findings or unexplained acidosis. Salicylates can cause a mixed acid-base disorder, often combining respiratory alkalosis with metabolic acidosis.
Key points for differentiation include:
- Diabetes, fasting, or alcohol use in the history for ketoacidosis Established kidney disease, low urine output, or rising creatinine for renal failure Exposure history, altered mental status, or visual symptoms for toxic alcohols Tinnitus, hyperventilation, or mixed respiratory findings for salicylates
In shock, these causes may coexist with lactic acidosis. As an example, a septic patient with renal dysfunction can have more than one acid-base disorder at once. This is why the high anion gap should always trigger broader diagnostic reasoning rather than a single-track conclusion.
What Is a Expected Anion Gap Suggest in Shock?
A typical anion gap cannot eliminate serious acidosis in shock. It may indicate non-anion gap metabolic acidosis, which often comes from bicarbonate loss rather than rise of unmeasured acids. In the unstable patient, this can occur with diarrhea, renal tubular acidosis, or chloride-heavy fluid administration causing hyperchloremia.
Normal-gap acidosis is important because it can occur alongside shock-related hypoperfusion. For example, a patient may have received substantial chloride-containing fluids during resuscitation and develop a non-gap metabolic acidosis even as the initial perfusion deficit resolves. In other cases, diarrhea or renal tubular dysfunction may be the primary acid-base disorder while shock is the broader clinical context.
Do not assume a normal gap means the situation is benign. It may simply mean the current problem is not increase of unmeasured acids. The bicarbonate can still be low, the pH can still be acidemic, and the patient can still have marked organ stress. Always check the arterial blood gas, clinical trend, and response to resuscitation.
How Can Albumin Levels Influence Anion Gap Interpretation?
Low albumin may render the anion gap seem incorrectly normal or only mildly elevated. Albumin is a key unmeasured anion, so when it is low, the measured gap decreases even if clinically important acids are present. This is particularly important in critical illness, where low albumin is common and can alter acid-base balance interpretation.
Albumin correction helps adjust the gap upward when albumin is low. That adjustment is crucial because an uncorrected result can miss a true high-gap process. In a patient with shock, this can postpone identification of lactic acidosis or another acid-base disorder that needs urgent attention.
Think about albumin correction when the result does not fit the patient’s condition. If the patient appears severely ill but the gap is “normal,” low albumin may be hiding the abnormality. Correcting for albumin gives a more accurate picture of acid-base balance and helps distinguish a genuine normal-gap state from a masked high-gap state.
In practice, albumin should be assessed alongside the anion gap calculator result, the serum bicarbonate, and the arterial blood gas. That combined view is more reliable than any single number.
Which Additional Labs Assist Interpret Shock and Acid-Base Status?
The anion gap is just one piece of the acid-base assessment. In shock, several additional labs help define the problem and direct resuscitation. The key are lactate, arterial blood gas, base deficit, and serum ketones.
Lactate is especially helpful because it indicates the severity of hypoperfusion and the degree of oxygen debt. An elevated lactate is consistent with lactic acidosis, though the exact source still requires clinical interpretation. The arterial blood gas displays pH, PaCO2, and bicarbonate, helping identify whether the patient has a simple metabolic acidosis or a mixed disorder with respiratory compensation. Base deficit gives another way to quantify metabolic acidosis and can help follow response over time. Serum ketones are important when ketoacidosis is possible.
Other supportive data may include creatinine, glucose, osmolar gap if toxic alcohols are a concern, and repeat electrolytes to observe the changing serum chemistry. In critical care, a single snapshot is rarely enough. The broader lab pattern is the most reliable way to connect the anion gap to the actual cause of shock.
When Is It Time to Recheck the Anion Gap in Shock?
Repeat the anion gap when the patient is receiving active emergency treatment, when the cause of shock is still being determined, or when treatment is underway and you need serial assessment. Repeated checks is especially useful if the initial gap is high, if lactate is elevated, or if the clinical response is not clear.
A falling gap can be a reassuring sign that the metabolic derangement is gettting better. In lactic acidosis, for example, the gap may fall as perfusion gets better and oxygen delivery is restored. In ketoacidosis, it often closes as insulin and fluids correct the metabolic process. In toxic ingestion, the pattern may evolve otherwise, but trend monitoring still aids show whether treatment is working.
Review again sooner if the patient worsens, if new laboratory data do not match the bedside picture, or if a mixed disorder is suspected. In shock, the anion gap is most useful when it is paired with ongoing clinical assessment and a clear understanding of the compensatory response.
Typical Errors When Interpreting Anion Gap in Shock
One common pitfall is lab error. A hemolyzed sample, specimen mix-up, or older value can result in faulty interpretation. Another pitfall is overlooking mixed acid-base disorders, which are frequent in shock and can mask the actual process.
Ignoring albumin correction is a common oversight. A low albumin can make a concerning high-gap acidosis appear less severe than it really is. The reverse can also occur: a patient can have both lactic acidemia and hyperchloremic acidosis, which may somewhat cancel out each other and produce a artificially small gap.
The delta-gap is useful when a mixed acid-base disorder is being suspected. It contrasts the change in anion gap with the difference in bicarbonate and can indicate whether there is an additional metabolic alkalosis https://anion-gap-formula266.raidersfanteamshop.com/how-lactic-acidosis-changes-the-anion-gap or a different non-gap acidosis. This is helpful in undifferentiated shock, where several processes may be present at the same time.
Other pitfalls include missing the overall clinical picture, failing to remember that shock itself may drive lactic acidosis, and relying on one isolated value rather than the full pattern. Proper acid-base interpretation requires the electrolyte panel, arterial blood gas, lactate, and bedside hemodynamics to be reviewed together.
FAQ: Anion Gap in Shock
What does a high anion gap mean in shock?
A high anion gap in shock usually means unmeasured acids are building up, usually from lactic acidosis due to tissue hypoperfusion. It can also reflect ketoacidosis, renal failure, toxic alcohols, or salicylates, so the result should be interpreted with the clinical picture and other labs.
Can shock cause a normal anion gap metabolic acidosis?
Yes. Shock can coexist with normal anion gap metabolic acidosis, especially if chloride-rich fluids are given during resuscitation or if there is another cause such as diarrhea or renal tubular acidosis. A normal gap does not rule out a significant acid-base disorder.
How does lactate affect the anion gap?
Lactate is an unmeasured anion, so when it rises it can increase the anion gap. Elevated lactate often reflects inadequate oxygen delivery, tissue hypoperfusion, or sepsis-related metabolic stress.
Why should albumin be considered when interpreting the anion gap?
Albumin is a major unmeasured anion. If albumin is low, the anion gap may appear falsely normal or only slightly elevated. Albumin correction helps uncover hidden metabolic acidosis, especially in critical illness.
What labs should be checked with an anion gap calculator in shock?
Along with the Anion Gap Calculator result, check lactate, arterial blood gas, base deficit, serum ketones, and repeat electrolytes including serum bicarbonate. These tests help define the acid-base disorder and distinguish lactic acidosis, ketoacidosis, renal failure, toxic alcohols, and other causes.